
In June 2025, shortly after submitting my thesis, Should Saunas be Prescribed?, I wrote a research proposal for a service evaluation of the community outreach and prescribing programme at Community Sauna Baths. My motivations for this were twofold: partly because I had bigger questions my thesis's scope couldn't hold, and partly because I was convinced, and remain so, that local saunas are playing a real role in boosting neighbourhood health here in the UK.
It was also clear to me that there was no universal framework for designing or implementing a prescribing programme for sauna bathing, let alone evaluating whether it works. And since I love tackling a wicked problem (yes, my degree was in Interdisciplinary Problems and Methods), I was right at home figuring out how to do it.
Without evidence of the social value saunas create, operators risk being unable to make the case to local authorities, NHS Trusts, and policymakers for why free or subsidised access is well worth funding. That case increasingly has to be made in a specific currency: the WELLBY, a wellbeing-adjusted life year (more on that later).
Working with Community Sauna Baths (CSB) and my co-researcher Freya Gascoyne, I designed and led the UK’s first service evaluation of an existing programme. We followed sixty-three bathers, referred by GPs, social prescribers, and community charities across five London sites, who were given ten free sauna sessions and asked three times over to name and rate the severity of their concerns and general wellbeing.
While the results are really encouraging, the more interesting question, to me, isn’t just whether sauna prescribing works. It’s how it works, for whom, and in what circumstances, which is the question this evaluation was actually designed to start answering, and the one I think the sector needs to get serious about.
What (sauna) social prescribing actually is
For anyone new to the term, or outside of the UK: social prescribing means a general practitioner (GP), a social prescriber (sometimes called a link worker), or a community organisation can refer you to non-medical support, instead of or alongside medication. It’s the NHS’s way of formally recognising that a lot of what affects someone’s health isn’t clinical. It might be loneliness, financial stress, or simply not having anywhere to go. Around 1 in 5 (200,000) GP consultations a day in England are for issues like these rather than a medical condition in the traditional sense (NHS England, 2023).
CSB’s Social Prescribing and Outreach Programme offers a package of ten free sauna sessions to people referred by GPs, social prescribers, and community organisations, as well as people who refer themselves. Crucially, the sessions aren’t scheduled for you. Bathers use their ten sessions at their own pace, whether that’s once a week for ten weeks, or spread out sporadically over a year.

Why evaluate sauna prescriptions, and why now
Well, there are several overlapping industry and policy signals driving the need to document sauna prescriptions properly.
1. Sector growth, including new large-scale entrants:
UK public saunas have grown from around 45 sites in 2023 to roughly 600 by mid-2026. Some of that growth is coming from new entrants: Therme Manchester, a 28-acre site at Trafford City, is on track to become the world's largest bathing and wellbeing attraction when it opens, targeted for late 2028, roughly 65,000 square metres, around 30 heat rooms including saunas, and a budget that's already grown from an original £175m estimate to £500m. Therme's own stated strategy, "90:90," is to get 90% of the UK population within a 90-minute drive of one of their sites, opening a new one roughly every two years over the next twelve.
2. Policy shifts from hospital to community: Neighbourhood Health
At the same time, the NHS’s 10-Year Health Plan and the accompanying Neighbourhood Health Guidelines are pushing hard on a shift from hospital-based treatment to community-based prevention, with social prescribing named as the main mechanism connecting the health system to community support. The VCSE sector (where saunas sit) is named as an important pillar of the framework. A major NIHR-funded evaluation of the link worker rollout found small but real improvements in patient experience, though it couldn't confirm the hoped-for drop in loneliness and isolation.
3. New ways of measuring wellbeing and social value: WELLBY’s
In 2021, HM Treasury included a new measure in the Green Book, the official guidance UK government departments use to appraise and evaluate policy: the WELLBY, short for Wellbeing-Adjusted Life Year. One WELLBY is a one-point change in self-reported life satisfaction, on a 0–10 scale, for one person, for one year- a live, government-recognised way to put a number on social value that didn't really exist before.
The Wellbeing Adjusted Life Year (WELLBY) sits alongside the NHS’s QALY, the Quality-Adjusted Life Year that NICE uses to decide whether a drug or treatment is worth funding, except WELLBY measures wellbeing rather than health, and HM Treasury uses it to appraise the kind of community and social programmes QALY was never built to capture. The 2026 Green Book now references it formally. It isn’t a government-only tool either: State of Life, the organisation behind it, designed it to be simple and cheap enough for small charities and community organisations to use, once they’ve established that their intervention actually has an effect. WELLBY is becoming the currency social value gets judged in, and it’s built to be usable by an organisation the size of a single community sauna, not just a national programme.
TLDR: I see sauna operators needing to translate their social value using WELLBY sooner rather than later.
How we measured the programme’s impact
We used a tool called MYCaW®, which stands for Measure Yourself Concerns and Wellbeing. The MYCaW® is a patient-centred questionnaire designed specifically to assess socially prescribed interventions. Participants identified one to two personal concerns they wanted to focus on through the programme, then rated how severe those concerns felt on a 0–6 scale, and rated their general wellbeing the same way. Zero is best, six is worst (backwards, I know).
Why didn’t I use the WELLBY framework?
The WELLBY model is deliberately general, a standard unit built so a sauna programme, a housing scheme, and a community choir can all be compared in the same funding conversation. Before anyone can credibly say what a sauna prescription is “worth” in WELLBYs, someone has to establish that it works, how it works, for what kinds of people and conditions, and under what circumstances.
Participants completed the MYCaW® at three points: immediately before their first sauna session, immediately after that first session, and again roughly ten weeks later, once their ten sessions were used up or the prescription was otherwise considered complete.
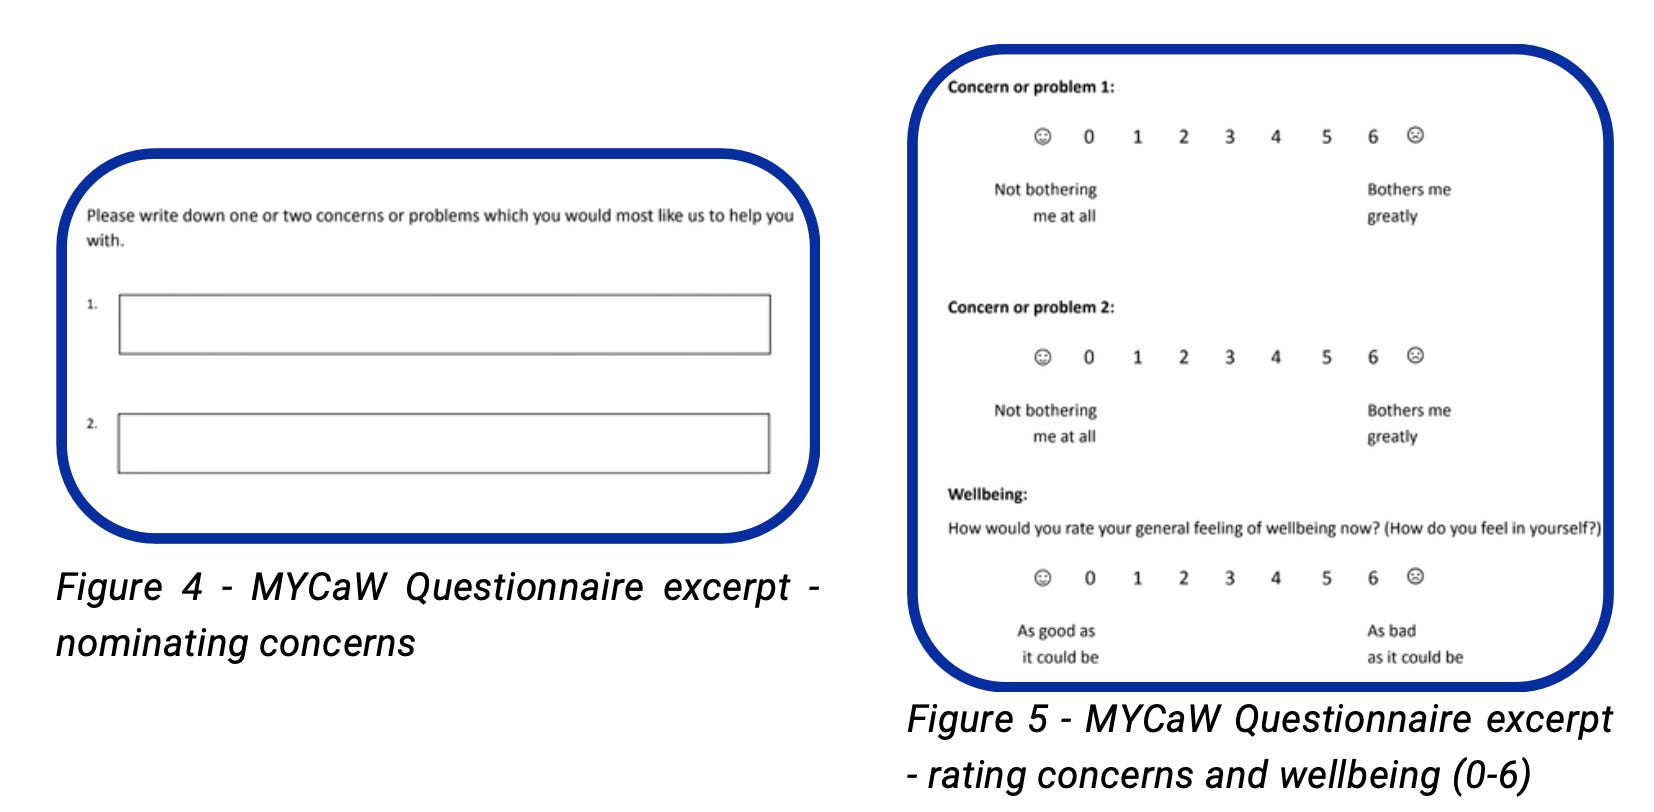
Alongside this, we ran a sense-making workshop with CSB’s Community Officers, the staff who actually deliver the programme and collect the questionnaires day to day. This wasn’t part of the original plan. It emerged as we realised that the people running the programme were noticing patterns that MYCaW® alone couldn’t tell us.
Who took part
Sixty-three participants took part, 26 men and 37 women, referred by a mix of GPs, social prescribers, and community charities. Despite using convenience sampling (participants opted in when starting their prescription, rather than being recruited through a formal sampling frame), the group was well spread across age and ethnic background.
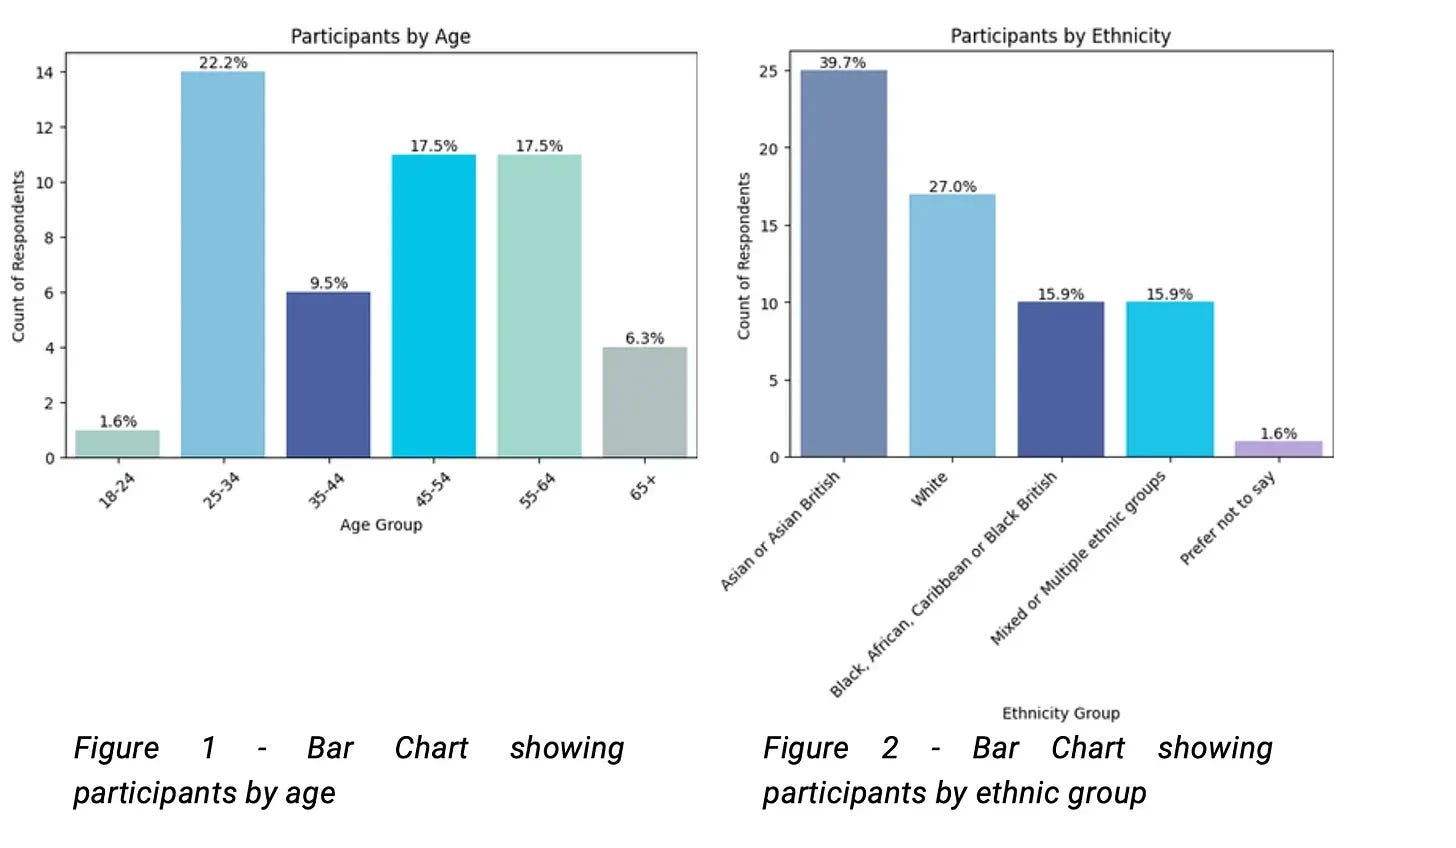
Of the 63, 92.06% (58 people) completed both the initial questionnaire and the first follow-up. That’s a strong response rate, helped by the fact that those two were completed on the same day, directly before and after the first sauna session. Retention across the full programme, including the final follow-up roughly ten weeks later, was lower, at 42.8% (27 people). Participants attended an average of six sessions during the ten-week window, out of a possible ten.
What people came in with, and who benefited most
Across the 63 participants, 107 individual concerns were shared, covering 56 distinct types, which we grouped into seven categories:
pain and musculoskeletal issues
stress
mental health
social isolation and loneliness
sleep
substance use and addiction
long-term health conditions
Pain and musculoskeletal concerns were the most common by some distance (42 mentions), followed by stress (23), mental health (17), social isolation and loneliness (11), and sleep (5).
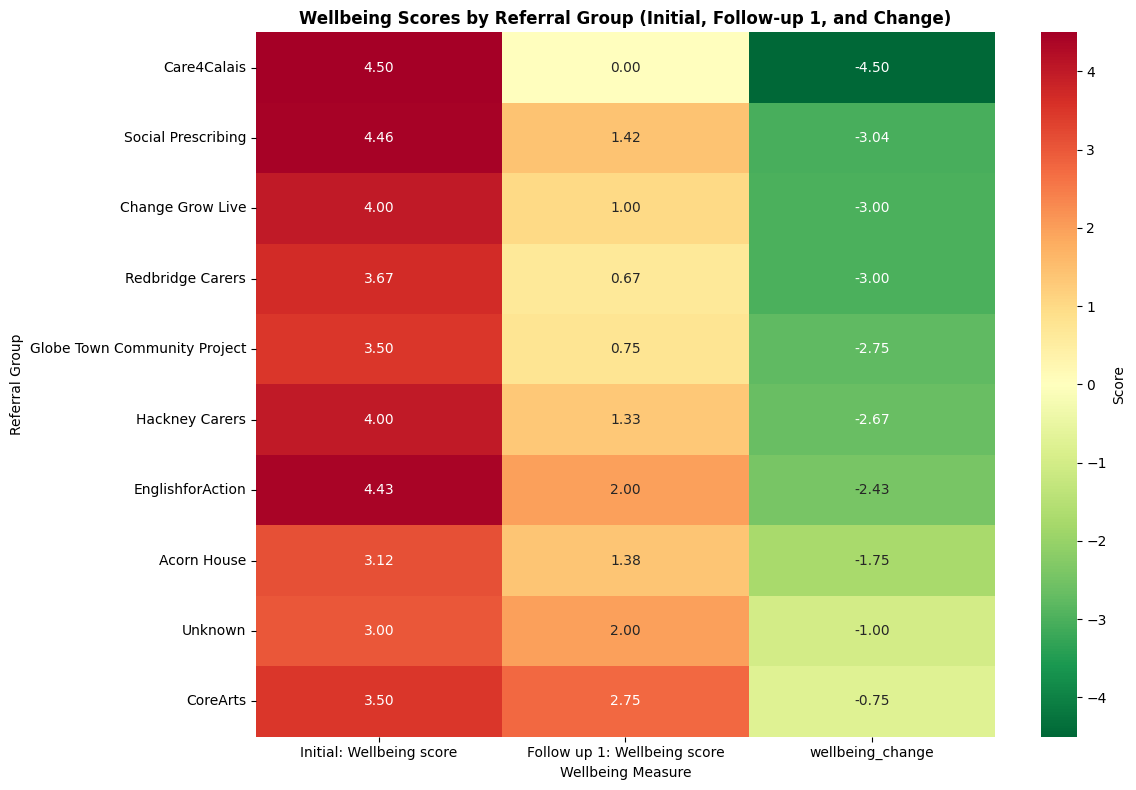
When we looked at community groups, those who started the programme with the highest distress tended to improve the most. Care4Calais and the general Social Prescribing referral group (first two rows in the heat map below) both began with the worst wellbeing scores in the cohort and reached close to 0, the best possible score, after just one sauna (follow-up 1).
When we looked at concern category instead of referral group, stress and social isolation or loneliness showed the biggest wellbeing gains for people’s primary concern (score changes of 3.85 and 3.5 respectively), and long-term health conditions and social isolation or loneliness showed the biggest gains for people’s secondary concern (4.00 and 3.43).
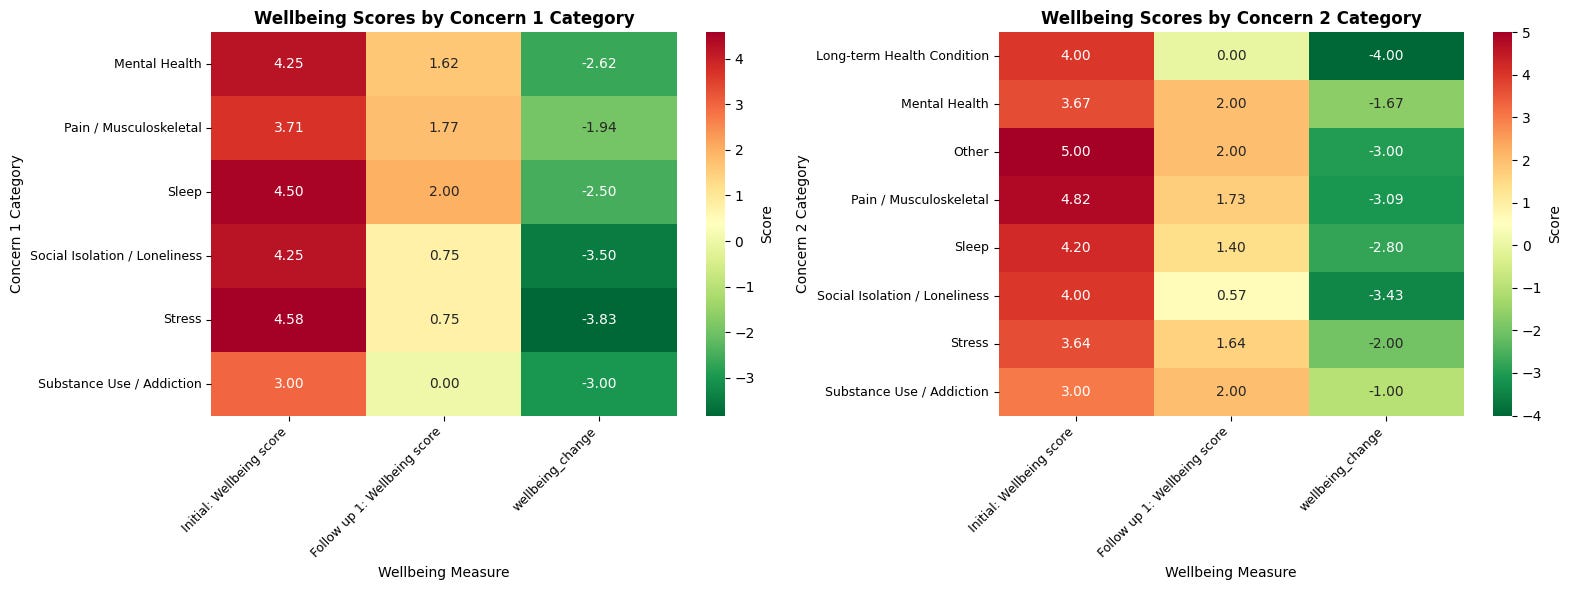
I want to be careful here: these are correlations, not causal proof.
That said, these findings are a genuinely useful signal for where sauna prescribing might do the most good, and could help CSB and similar programmes think more deliberately about who they prioritise for referral.
What we found
The programme produced large, statistically significant improvements across primary and secondary concerns, and general wellbeing. The significance was p≤0.001, meaning there’s less than a 1-in-1,000 probability these results happened by chance.
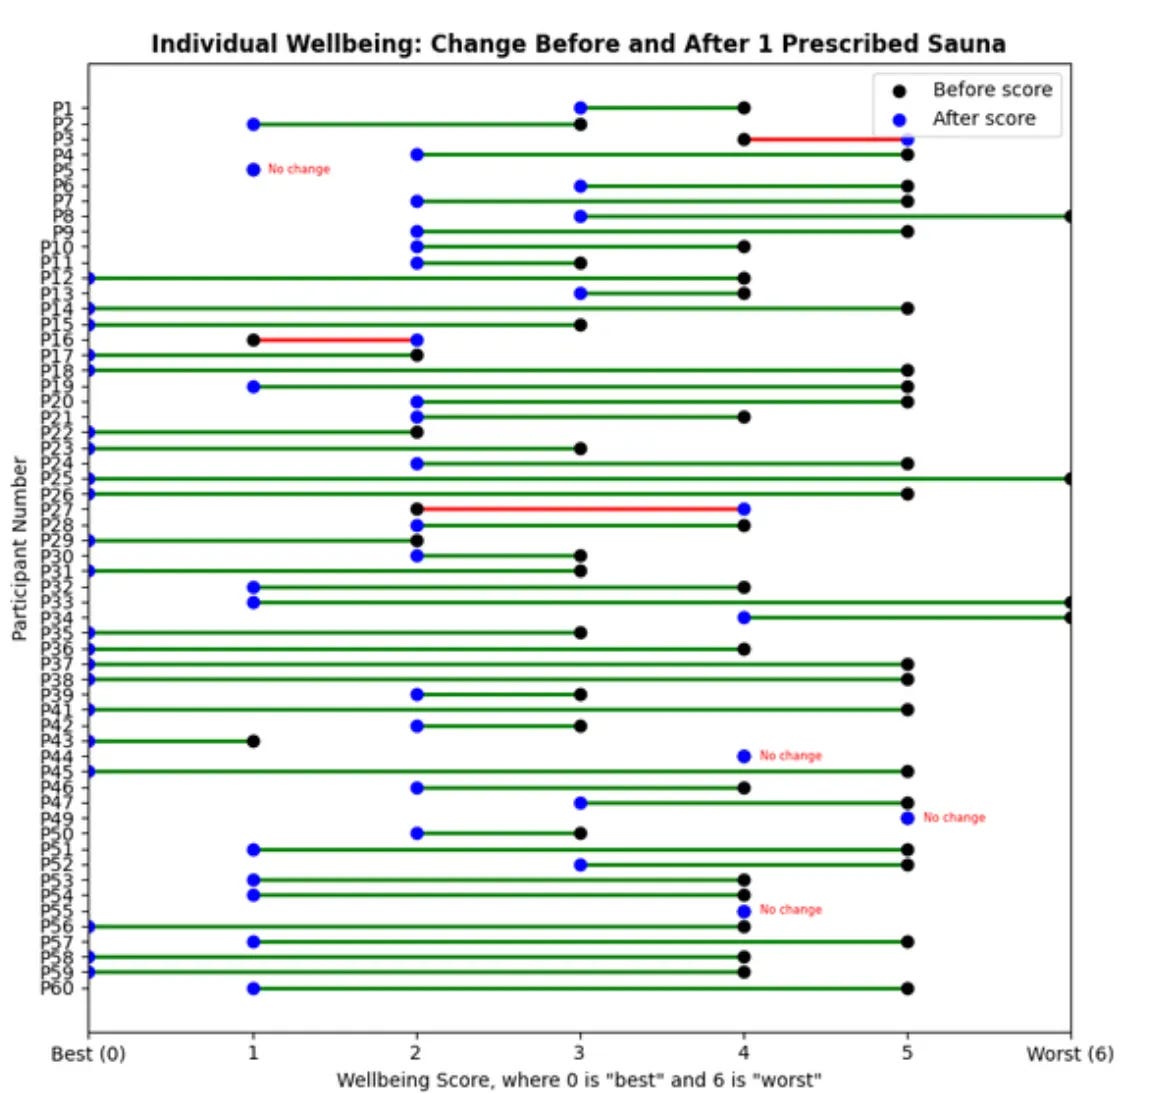
After a single sauna session, concern severity dropped by an average of 2.9 points, moving participants from a moderate-to-high severity range (around 4.6–5.1) down to around 1.8–2.2. General wellbeing improved by an average of 2.6 points. Eighty-six percent of participants crossed the threshold for a meaningful improvement in their primary concern, 96% did for their optional second concern, and 88% improved meaningfully on wellbeing. Nobody’s nominated concerns got worse after that first session, though a small minority, 5%, reported a decline in general wellbeing.
For the 27 people who completed the full ten-week programme, the improvements were even larger. Concern severity fell by an average of 3.8 points for the primary concern and 4.0 for the secondary one, landing close to the best possible score on the scale. Wellbeing improved by an average of 3.0 points, with 93% improving meaningfully and only 4% declining. The overall MYCaW profile score, which combines concerns and wellbeing into a single measure, moved from an average change of −2.8 after one session to −3.5 after the full programme.
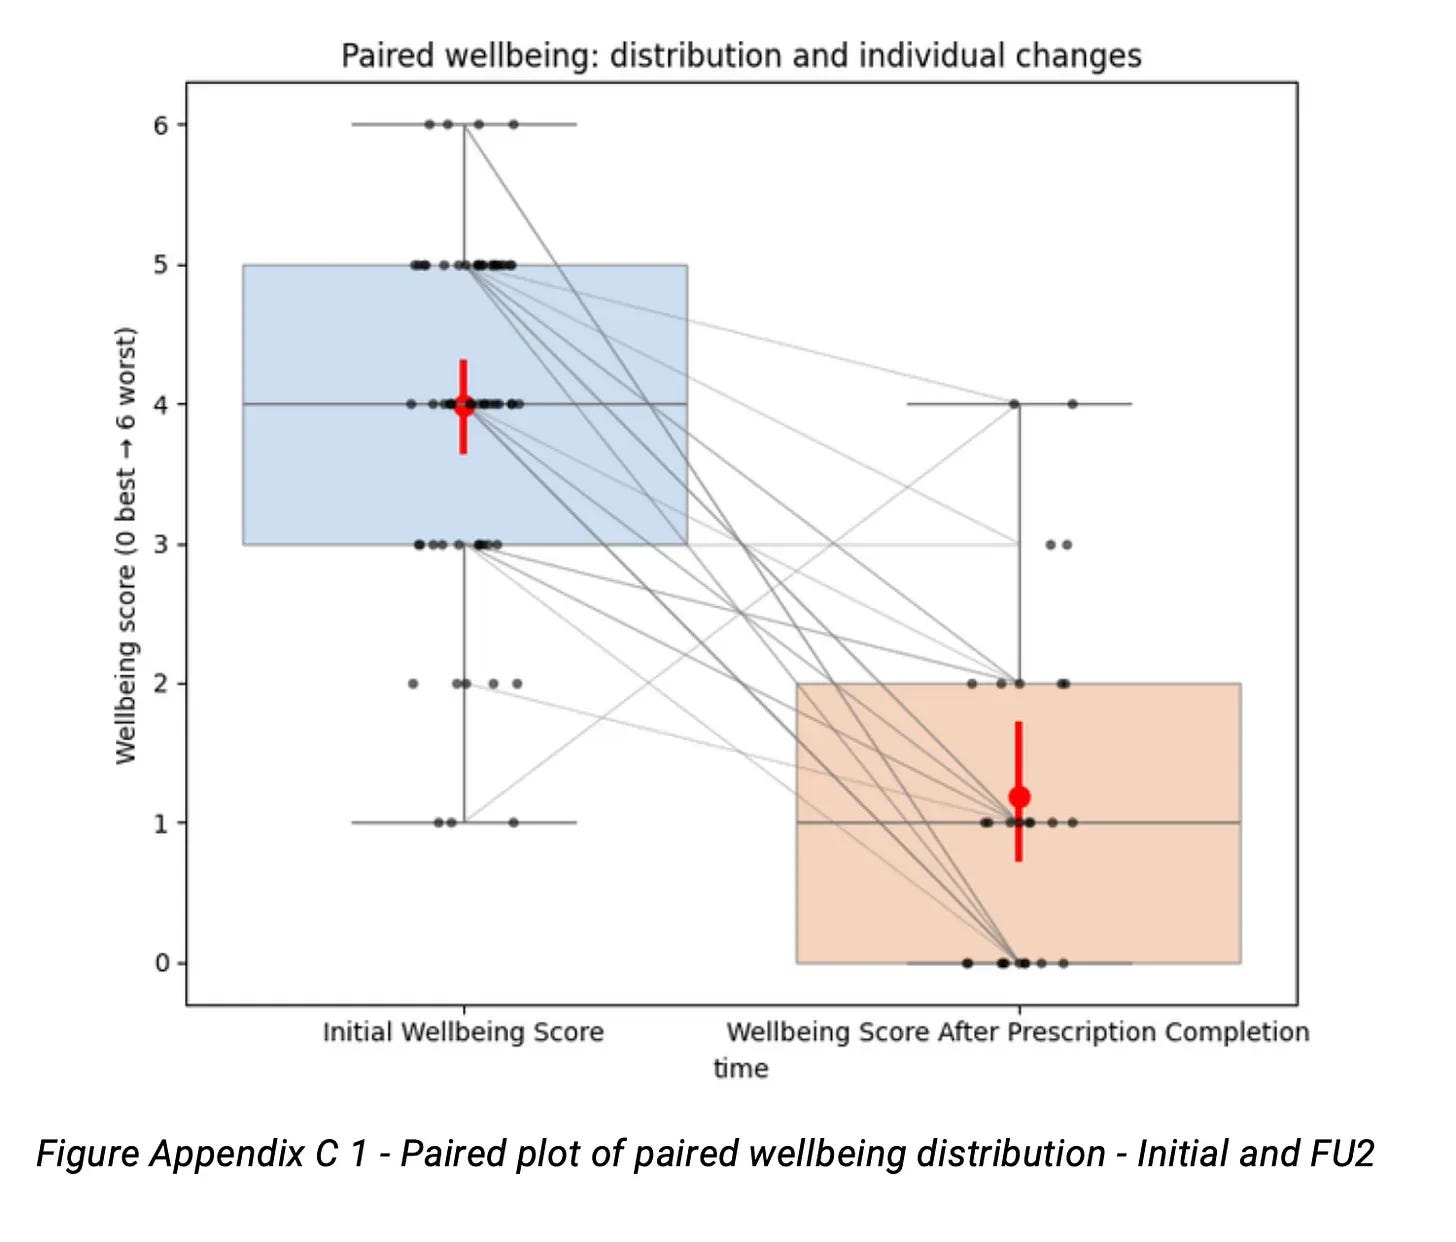
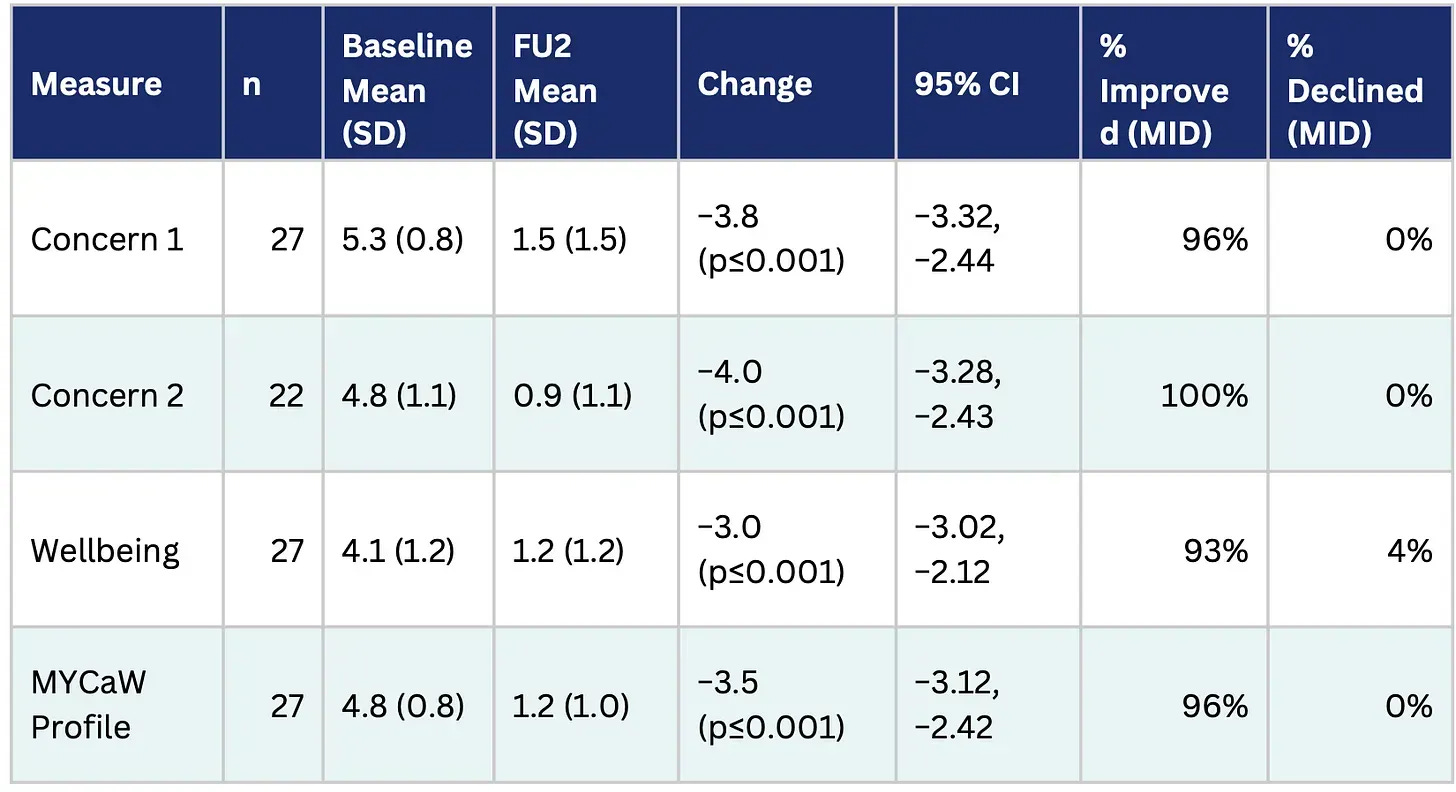
This comparison suggests the benefit isn’t just a one-off from a single sauna session. Instead, improvements in concern severity and wellbeing build with repeated use. Aka dose matters. This supports CSB’s current model of offering a minimum of ten sessions, used at the bather’s own pace, rather than a single session, or 10 sessions within a predetermined timeframe.
What the people delivering the programme told us
Socially prescribed bathers attended more consistently when they came as part of a group rather than solo. This tracks with our separately published research showing that social connection and belonging within sauna groups significantly boost physical and mental wellbeing (Newson et al., 2026).
Staff also noticed that people responded better to structure than to complete openness. Booking regular slots from the start, rather than leaving it entirely open-ended, supported better attendance.
Practical barriers came up repeatedly: transport costs and distance from a sauna site, people not having access to, or checking emails (missing reminders).
The limitations, honestly
This was a service evaluation, not a clinical trial. There’s no control group, so while the correlations here are statistically significant and consistent, we can’t claim causation in the clinical sense. Attrition was a real challenge, with well under half the original 63 completing all three questionnaires, and the workshop suggested this was driven by a mix of the programme’s intentionally flexible, self-paced structure and genuine practical barriers like transport, language, religious holidays, and life circumstances. The timing of the final follow-up also varied a lot between participants, which complicates direct comparison across the group.
None of this undermines the core findings, but it does shape how confidently we can generalise it, and it’s exactly why the next phase of this work matters.
What’s next: the formula and dosage question
The questions I keep coming back to:
If a single sauna session produces a meaningful improvement, and ten sessions produce a bigger one, what’s the actual relationship between dose and benefit? How often, for how long, and for whom does this work best? Should we include a sauna ritual (or several) into a prescription? Does someone dealing with chronic pain need a different pattern of sessions than someone dealing with social isolation?
I think this evaluation answers the question “is sauna a legitimate social prescription”, pretty convincingly. But how do we prescribe it with the same kind of specificity we’d expect from any other intervention: tailored to the person, their concern, and their circumstances, rather than a “ten saunas for everyone model?
Answering that properly needs longer follow-up periods, a wider range of programme sites, and a study designed from the outset to test different dosing patterns against each other. That’s the work I’m building towards now.
Thank you
This evaluation only exists because of the people who made it possible. Huge thanks to Community Sauna Baths, my co-researcher Freya Gascoyne, and the 63 participants who shared their experiences and their MYCaW scores with honesty and courage.
If this was useful, the most helpful thing you can do is send it to one person: your GP or doctor if you’re outside of the UK, the person who runs your local sauna, or whoever's deciding what gets funded in your world. And if you've got a view on where to go next, say so in the comments, I read all of them.
This is That Sauna Girl, where I write about the evidence behind sauna, for the people building this sector and the people bathing in it. If you want to see where the dosage question goes next, subscribe, that's where I'll be working it out in public.
If you’re a GP, social prescriber, sauna operator, NHS trust, local authority, or researcher who wants to be part of figuring out the dosage question, I’d love to hear from you. Get in touch here.
Rachael

This is fantastic work, congratulations and thank you for sharing. I’m opening a sauna in Ireland and really want to figure out how to offer this kind of service here. I’m a massive CSB fan so want to adopt a similar thesis. If you are aware of any social prescribing groups over here I should be talking to, or where I should start, I’d be very appreciative of the referral.
super cool work. Do you study to explore sauna + cold therapy?